
Article
Questions to ask a clinician before considering methylene blue
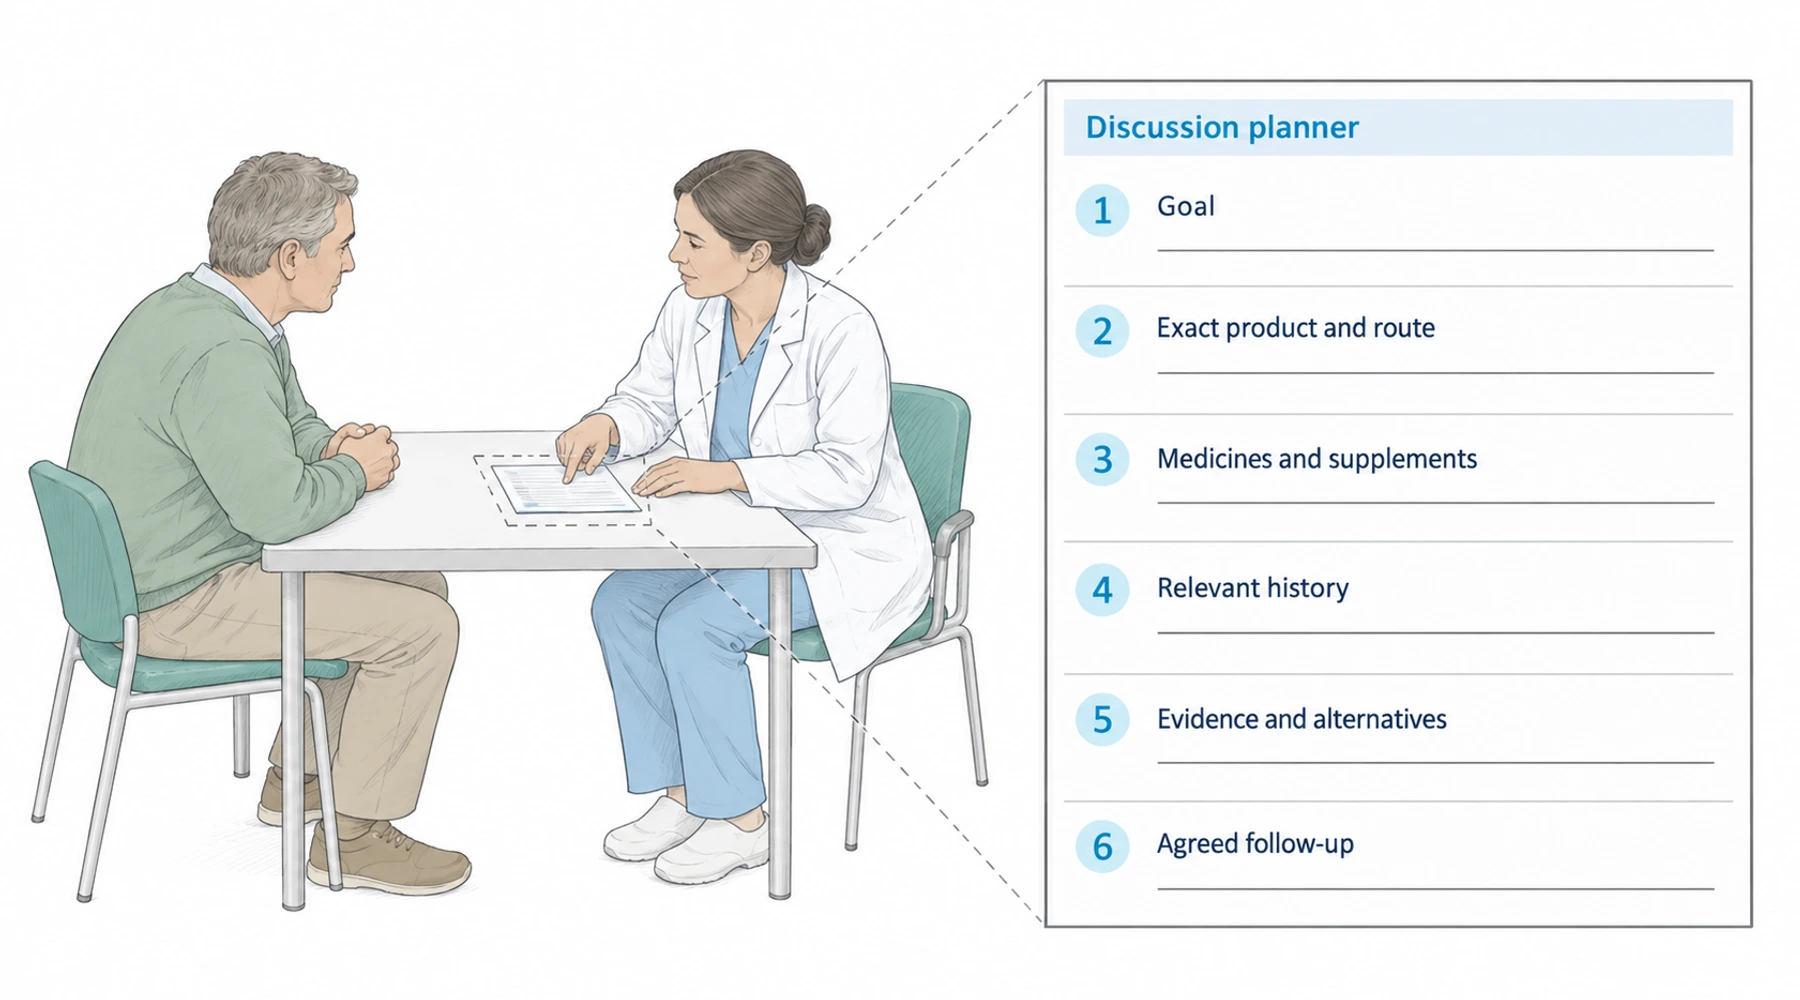
The most useful opening question is specific: “I want help with this problem, and I have seen methylene blue recommended. Does the evidence apply to me?” That gives your clinician a goal to investigate and a claim to evaluate. Asking only whether methylene blue is “good” leaves both undefined.
Bring the exact product label, a current medicine and supplement list, and the source of the recommendation. Open the one-page clinician conversation planner and print it before your appointment. It provides space to record information and decisions. Completing it does not establish that a product is appropriate for you.
1. Describe the problem before discussing the product
Write one sentence about what you want to change. “I lose track of tasks at work” provides more information than “I want better brain function.” Add when the problem began, whether it is changing, and what it prevents you from doing. If you already have a diagnosis, record it separately from symptoms that have not been assessed.
Ask: “Does this need further assessment before we discuss treatment?” A product recommendation can make a conversation begin too late, after assuming that the cause of a problem is known. Your clinician may need to investigate the symptom, review an existing treatment, or clarify the goal first.
Prioritizing concerns and bringing relevant records follows the National Institute on Aging's appointment-preparation guidance. Put the question that matters most at the top of your page.
2. Identify the exact proposal
“Methylene blue” names a substance, not a complete treatment. Photograph the front and back of the container, including ingredients, concentration, manufacturer, intended use, and lot number. Record the proposed route, such as oral use or administration in a clinic, without trying to convert a seller's directions into a personal regimen.
The U.S. PROVAYBLUE prescribing information describes an intravenous prescription medicine for acquired methemoglobinemia in adults and children. That label does not establish the benefit of a consumer bottle for memory, energy, or another proposed goal.
Ask your clinician to identify which product and use are actually being discussed. If a seller says “pharmaceutical grade,” bring the underlying documentation and ask what it establishes. A useful product-quality review separates the identity and testing of a material from evidence for treating a person.
3. Bring the whole medicine list
Include prescription medicines, nonprescription products, vitamins, herbs, and supplements. Add the amount you currently take, timing, occasional use, and recent changes. Bring packaging if a combination product's ingredients are unclear. Ask a pharmacist to review the list alongside the exact methylene blue product and proposed route.
There is a specific reason to make this comprehensive. The PROVAYBLUE interaction warnings describe potentially fatal serotonin syndrome with serotonergic medicines and opioids; they also identify dextromethorphan, an ingredient in some cough medicines. A medicine used only occasionally can therefore matter. These examples are not a complete interaction screen.
Do not stop a prescribed medicine or invent a waiting period to accommodate methylene blue. Ask the prescriber and pharmacist to resolve any proposed changes. Our explanation of methylene blue and medicine interactions can help you prepare the terminology for that discussion.
4. Ask which history needs review
Bring relevant diagnoses, allergies, previous reactions, and available test results. State what you do not know rather than treating missing information as a reassuring answer.
The prescription label contraindicates PROVAYBLUE in G6PD deficiency because of hemolytic anemia risk and in severe hypersensitivity. It also addresses pregnancy, breastfeeding, and kidney or liver impairment. Ask which parts of your history require assessment and whether existing results are sufficient.
This is a conversation about clinical relevance, not a list of boxes that grants permission to proceed. A clinician must interpret the history together with the purpose, product, route, and other treatments.
5. Bring one claim and its supporting study
Save the paper title, link or DOI, and the particular sentence you want evaluated. A screenshot of a graph without its caption, methods, or study population usually leaves the essential question unanswered: what was actually tested?
Use the following prompts to keep the discussion focused. They build on NCCIH's guidance for interpreting health research.
| What to ask | Why the answer changes the decision |
|---|---|
| Was this tested in people with my condition? | A laboratory finding or a different patient population may not answer your clinical question. |
| Did the study test this formulation and route? | Sharing an ingredient name does not make two interventions equivalent. |
| What improved, and by how much? | A test result may have a different meaning from better daily functioning. |
| What was the comparison treatment? | Improvement over time alone does not show that the intervention caused it. |
| How long were participants followed? | Brief observation cannot establish durable benefit or long-term safety. |
| What remains unknown? | The uncertainty should be explicit before deciding what to do next. |
Choose the two questions most relevant to the claim. You do not need to conduct a literature review before asking for help.
6. Compare alternatives and agree on the next step
Ask what established options address the same goal, what further assessment could change the decision, and whether doing nothing new while gathering information is reasonable. The FDA's explanation of off-label prescribing makes an essential distinction: clinicians may prescribe an approved drug for an unapproved use when medically appropriate, but FDA has not established safety and effectiveness for that unapproved use. Ask what supports the proposed use in your circumstances.
If the evidence is uncertain, request a concrete answer: “Is the uncertainty about whether it works, whether it is safe for me, or whether this product matches the research?” Each gap requires a different next step. A safety concern calls for review; missing benefit evidence cannot be repaired by choosing a more impressive label.
Before leaving, record the agreed action, who is responsible, and when you will hear back. If treatment is proposed, ask how benefit and harm would be assessed, who handles new symptoms, and what would lead the clinician to reconsider it. If no treatment is recommended, record the reason and the plan for your original concern. The appointment is useful when you leave with an answer about that concern and a clear follow-up, whether methylene blue becomes part of the plan or not.