
Article
Methylene blue in fertility testing: what chromopertubation actually shows
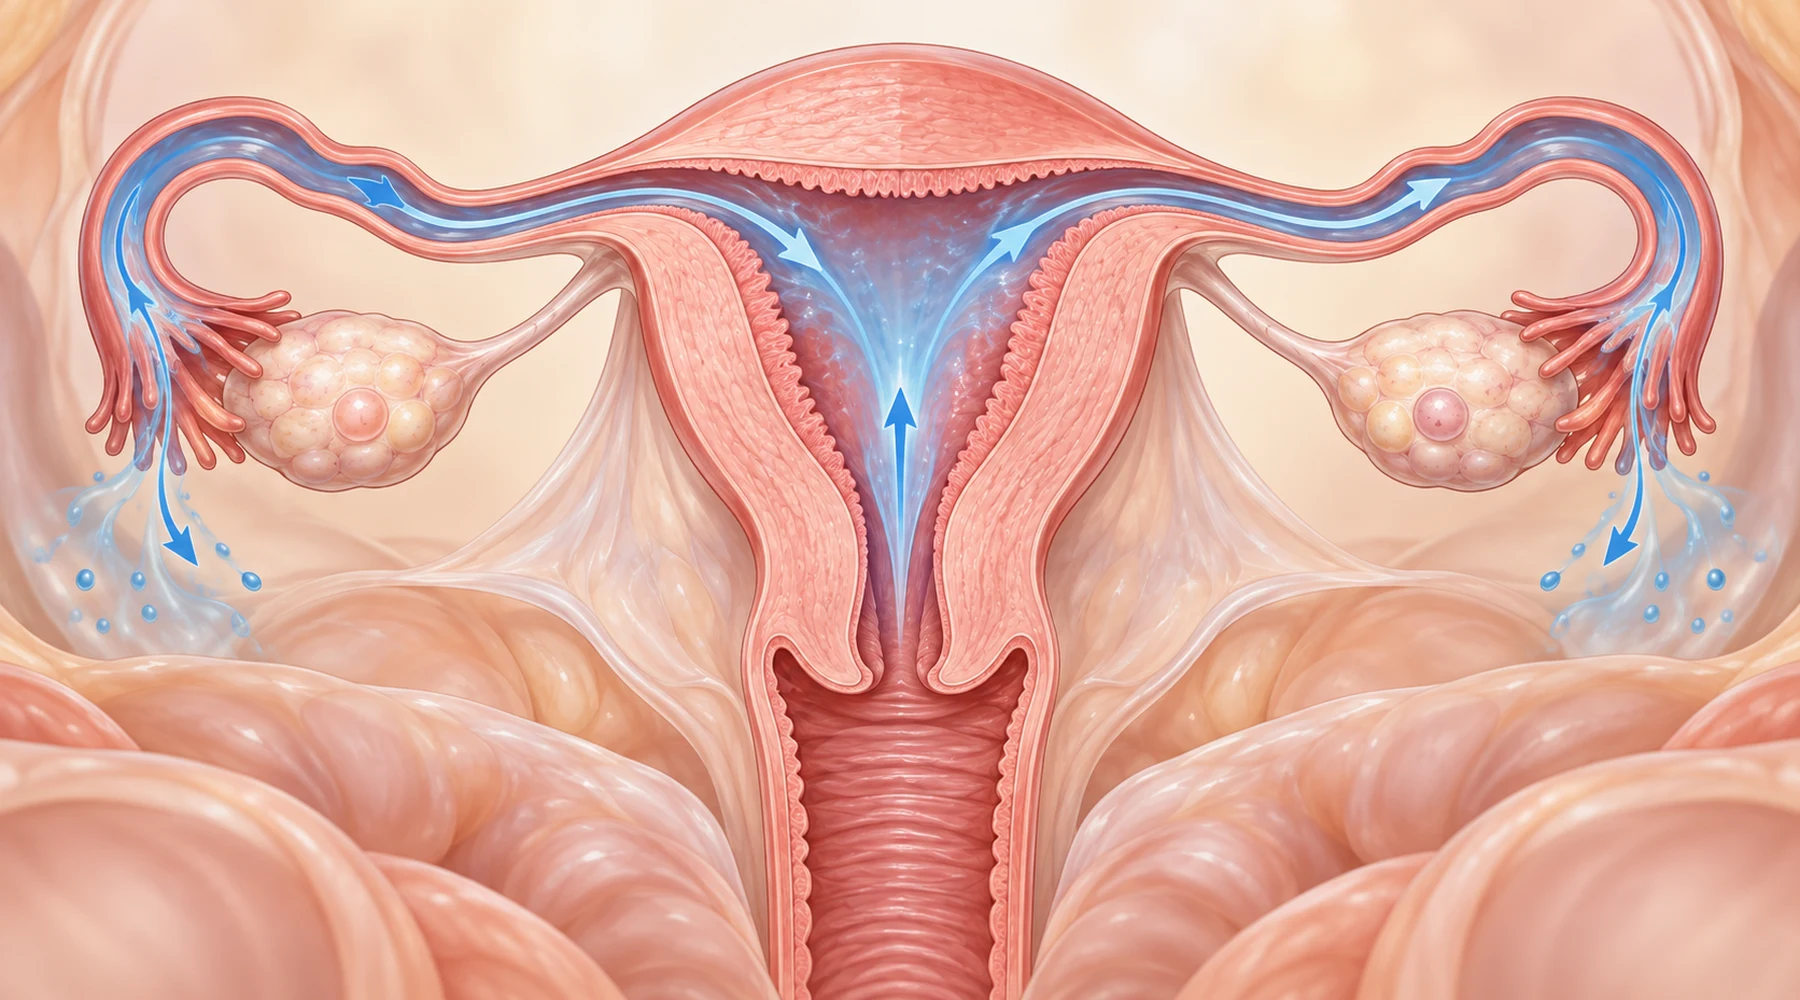
Search results for methylene blue fertility mix two different claims. One is that a blue dye test in the clinic can show whether fallopian tubes are open. The other is that taking methylene blue improves fertility, sperm, or egg quality. Only the first claim belongs to chromopertubation. The second was not tested and is not part of this procedure. That distinction organizes everything below.
The useful question is narrower. When blue dye is placed in the uterus under clinical conditions, and fluid is seen leaving through a tube, that tube is patent at that moment. When no flow is seen, the answer is less certain than it looks. A 2021 comparison of two dye test settings shows exactly where the reading holds and where it breaks.
The concept: a flow test, not a fertility treatment
Each fallopian tube is a narrow passage from the uterus toward the ovary. Chromopertubation tests one property of that passage: whether fluid can get through. Methylene blue is the marker that makes the flow visible, since its deep color stands out against pale tissue.
The setup is the same in both settings. Dye enters through the cervix into the uterine cavity and the clinician watches what happens next. Dye spilling from the far end of a tube means patent. Dye pooling and flowing back means apparently blocked. The reading covers transit, in one direction, on one day.
This is a clinician performed procedure. The office version happens during hysteroscopy, where a thin scope looks inside the uterus. The operating room version happens during laparoscopy, where a scope looks at the outside of the tubes and pelvis, usually under general anesthesia. Neither version is self administered, and neither delivers a drug meant to change fertility. The dye is a tracer that washes through. Descriptions of how methylene blue behaves as a dye help here, and the separate question of how to read methylene blue research explains why a laboratory effect never equals a clinical treatment.

Patent does not mean normal
Patency is one concept and tubal function is a larger one. A tube can be open yet fail at its job: infection or endometriosis can damage the cilia that move the egg while leaving the passage wide enough for dye, and scar tissue outside the tube can hold the ovary at a distance so the egg never enters despite free spill. Partial narrowing can pass a thin dye stream while blocking the larger egg.
So a patent result answers a small question with reasonable confidence: fluid crossed the tube. It does not certify the lining, egg pickup, or the surrounding pelvis. A blocked result is weaker still, because transient conditions can stop flow through an open tube.
What the 2021 study compared
The clearest head to head data come from a 2021 pilot study of 80 infertile women at AIIMS New Delhi, with full methods and results available in the open access text. Every participant was already scheduled for hysterolaparoscopy. Women with previously confirmed block, known hydrosalpinx, or acute pelvic infection were excluded.
Each woman had two dye tests in sequence. First, office hysteroscopy without anesthesia: diluted dye was introduced and each tubal opening was watched for visible flow plus clearing of blue from the cavity. Then minilaparoscopy under general anesthesia as the reference: dye went through an intrauterine catheter and each tube was judged by visible spill into the pelvis. Both tubes counted separately, giving 160 observations.
The reference test found 136 of 160 tubes patent (85 percent). The office test called 125 patent (78 percent). Agreement was good but asymmetric: 119 tubes patent by both, 18 blocked by both, 17 called blocked by the office test but patent at laparoscopy, and 6 called patent by the office test but blocked at laparoscopy. Against laparoscopy as reference, the office test showed 87.5 percent sensitivity for patency, 75 percent specificity, 95.2 percent positive predictive value, 51.4 percent negative predictive value, and 85.6 percent overall accuracy.
Read those numbers as a reader, not a statistician. A patent call from the office test was usually right. A blocked call was close to a coin flip: only about half of office blocked readings were confirmed at laparoscopy. That asymmetry is the single most practical fact in the paper.
Why an apparent block is the weaker result
The most ordinary reason is spasm. The uterine corner where the tube begins can contract briefly and pinch shut an open passage. Cold fluid and cramping pain are discussed in the paper as possible triggers. The contraction passes, but a reading taken during it looks identical to true obstruction, which is why an isolated proximal block on any single test is treated with suspicion.
Technique adds error too. Fast introduction causes backflow that mimics blockage, and a poor viewing angle can miss a thin spill. The study used one experienced surgeon throughout, so variation in ordinary practice is likely larger.
The clinical consequence follows directly. An apparent block on the office dye test is a reason to confirm, not a diagnosis to act on alone. Confirmation usually means the laparoscopic reference test or another tubal assessment chosen by the fertility team, interpreted alongside history, infection risk, and imaging. A methylene blue test of fallopian tubes rules patency in more strongly than it rules it out.
What dye flow cannot see
Chromopertubation measures transit. Several conditions that matter for fertility sit outside that view. Peritubal adhesions, bands of scar tissue around the tube, are invisible to the hysteroscope, which sees only the cavity and tubal openings. Laparoscopy sees them directly; in this study 4 of 80 women had adhesions found only at that stage, and earlier work shows they raise the chance of a falsely reassuring flow reading.
Hydrosalpinx, a tube swollen with fluid from distal blockage, is a similar blind spot: known cases were excluded, yet unrecognized hydrosalpinx appeared at laparoscopy in 7 of 80 women. Endometriosis, mucosal damage, and impaired egg pickup complete the list. That is why fertility guidelines describe chromopertubation as a maneuver performed when laparoscopy is otherwise indicated, as reflected in the ASRM committee opinion on infertility evaluation. The broader context of methylene blue safety data matters when any surgical assessment is weighed.
How it differs from the other tube tests
Hysterosalpingography (HSG) passes radiopaque contrast through the cervix and uses X-ray imaging to outline the cavity and tubes. It documents spill like chromopertubation but adds radiation, cannot inspect the outer pelvis, and shares the spasm problem at the uterine corner.
Saline ultrasound places sterile saline in the cavity while a vaginal probe images it. Plain saline imaging is mainly a cavity test: pelvic fluid suggests at least one tube is open but usually cannot say which one. Contrast ultrasound with foam or microbubbles tracks individual tubes and is the closer analogue of a dye test.
Safety and setting in plain terms
In the 80 patient study the authors reported no major or minor complications from either dye test. That reassures within a small pilot and says nothing about zero risk: case reports after chromopertubation describe rare hypersensitivity reactions, methemoglobinemia, dye entering blood vessels, and pulmonary complications, with incidence poorly quantified.
Two points follow. The laparoscopic version adds the ordinary risks of surgery and anesthesia, which is why it is reserved for cases where operative inspection is already planned. And nothing transfers to home use: concentration, sterility, placement, and emergency readiness sit with the clinical team.
The fair summary is therefore conditional. Chromopertubation with methylene blue shows whether fluid crosses a tube under observation, with a patent reading considerably more trustworthy than a blocked one. It does not measure tubal function, does not find every pelvic cause of infertility, and does not treat anything. Anyone offered the test should ask three questions: which setting is planned and why, what happens if the reading is blocked, and what additional findings would change the plan.